Skip to content
  • Categories
  • Recent
  • Tags
  • Popular
  • Users
  • Groups
Collapse
IMA HUB – Empowering Doctors & Hospitals

IMA HUB – Empowering Doctors & Hospitals

State_Tamil Nadu_Member

Private

Posts


  • IMA KPPS: Professional Protection Every Doctor Should Understand
    Admin IMA HubA Admin IMA Hub

    ksps (1).png

    Medical practice today involves not only clinical responsibility but also increasing legal, financial, and professional risk. Even when treatment is appropriate, a doctor may still have to respond to allegations, consumer complaints, or compensation claims.

    The IMA Karnataka Professional Protection Scheme (IMA KPPS) is a mutual support initiative of the IMA Karnataka State Branch designed to safeguard medical practitioners against legal expenses and compensation claims arising from professional negligence disputes. It supports members in handling litigation before District, State, and National Consumer Forums and provides protection up to ₹1 crore.

    Key benefits

    • Support through panel advocates and assistance with legal expenses
    • Option to engage one’s own lawyer, subject to KPPS rules
    • Protection against professional-negligence and CPA-related claims
    • Helps protect professional confidence, practice continuity, and personal assets
    • Individual-doctor benefit scheme; hospitals are not covered

    Who is eligible?

    The applicant should:

    • Be a Life Member of IMA
    • Be registered with the Karnataka Medical Council
    • Ensure that PG degree or diploma registration is included
    • Maintain continuous active membership to retain scheme benefits

    What should a member do after receiving a legal notice?

    The member should immediately contact the KPPS office and submit:

    • A copy of the legal notice or complaint
    • OP/IP case papers
    • Investigation reports
    • Treatment records

    The KPPS office reviews the matter, provides a panel of advocates, and supports the member in proceeding with the defence.

    Fee details

    At admission:

    • Admission fee: ₹100
    • Annual subscription: ₹2,000
    • Advance fraternity contribution: ₹1,000
    • GST and round-off: ₹600
    • Total: ₹3,700

    For subsequent years, the annual subscription is ₹500, while the fraternity contribution is decided and communicated for that year.

    Documents required

    • Duly filled and signed application form
    • IMA Life Membership Certificate
    • KMC Registration Certificate
    • Address proof
    • PAN card
    • Three passport-size photographs

    Contact

    IMA KPPS Registered Office
    1st Floor, IMA House,
    Alur Venkata Rao Road, Chamarajpete,
    Bengaluru – 560018

    Phone: 080-26705447
    KPPS Mobile: 9141546924
    Email: imakpps@gmail.com
    Website: www.imakppsbengaluru.org

    Discussion

    Are doctors in your branch adequately aware of professional-protection schemes such as IMA KPPS?

    What additional awareness, documentation training, or medico-legal support should IMA branches provide to members?

    Join the discussion and share your experience.


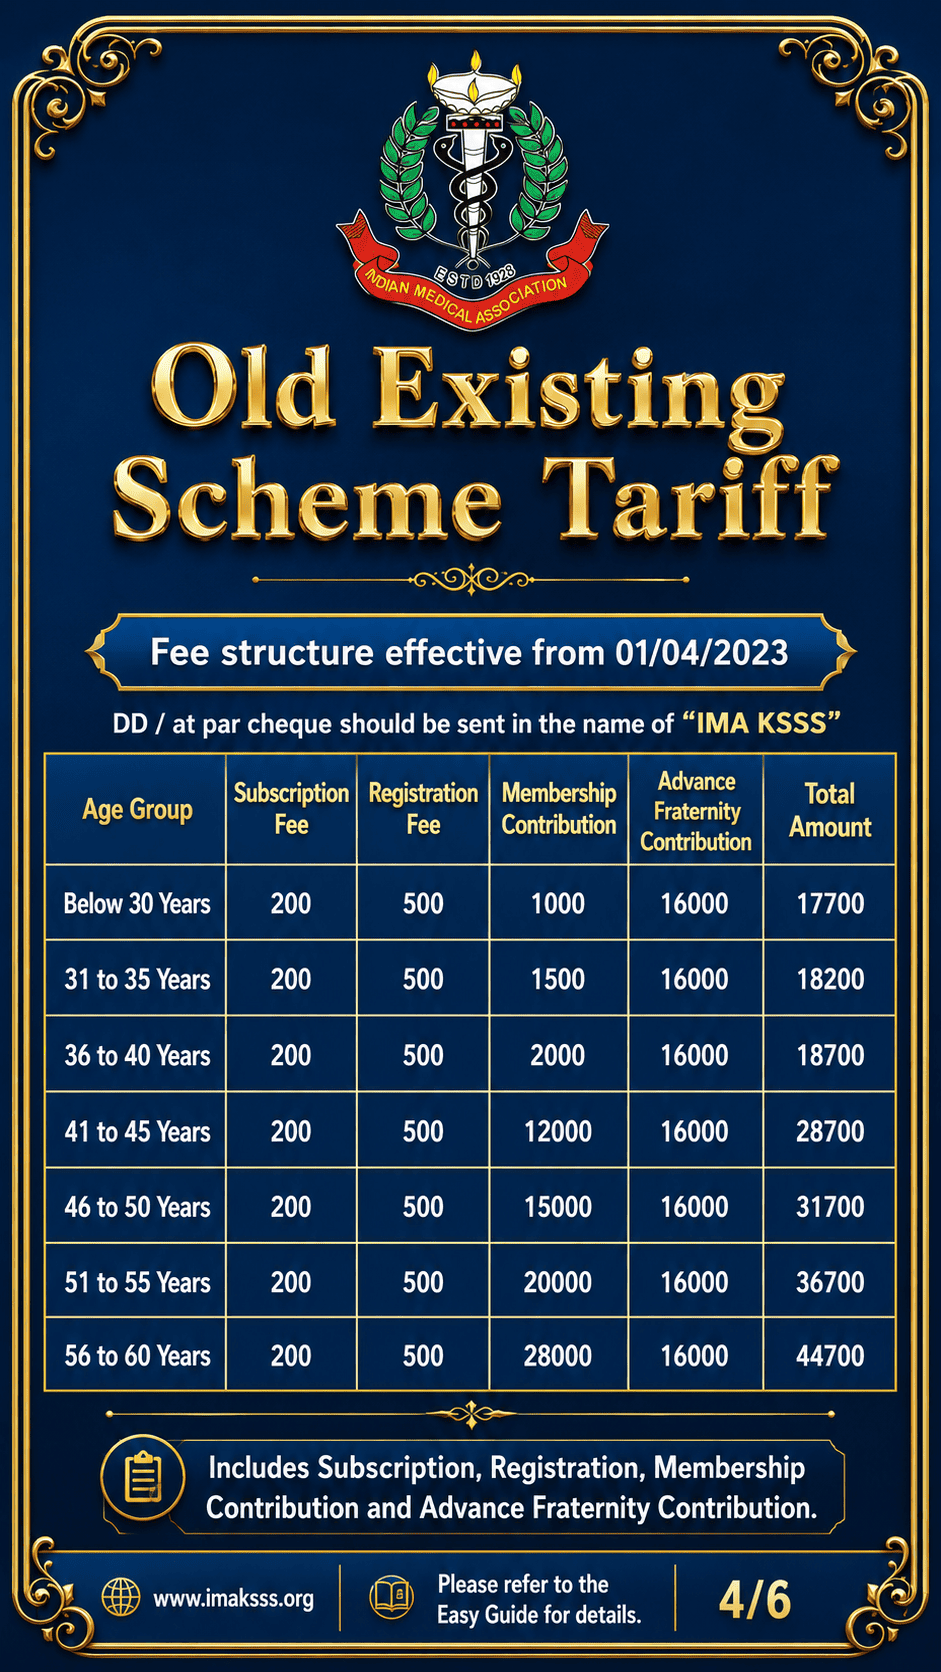
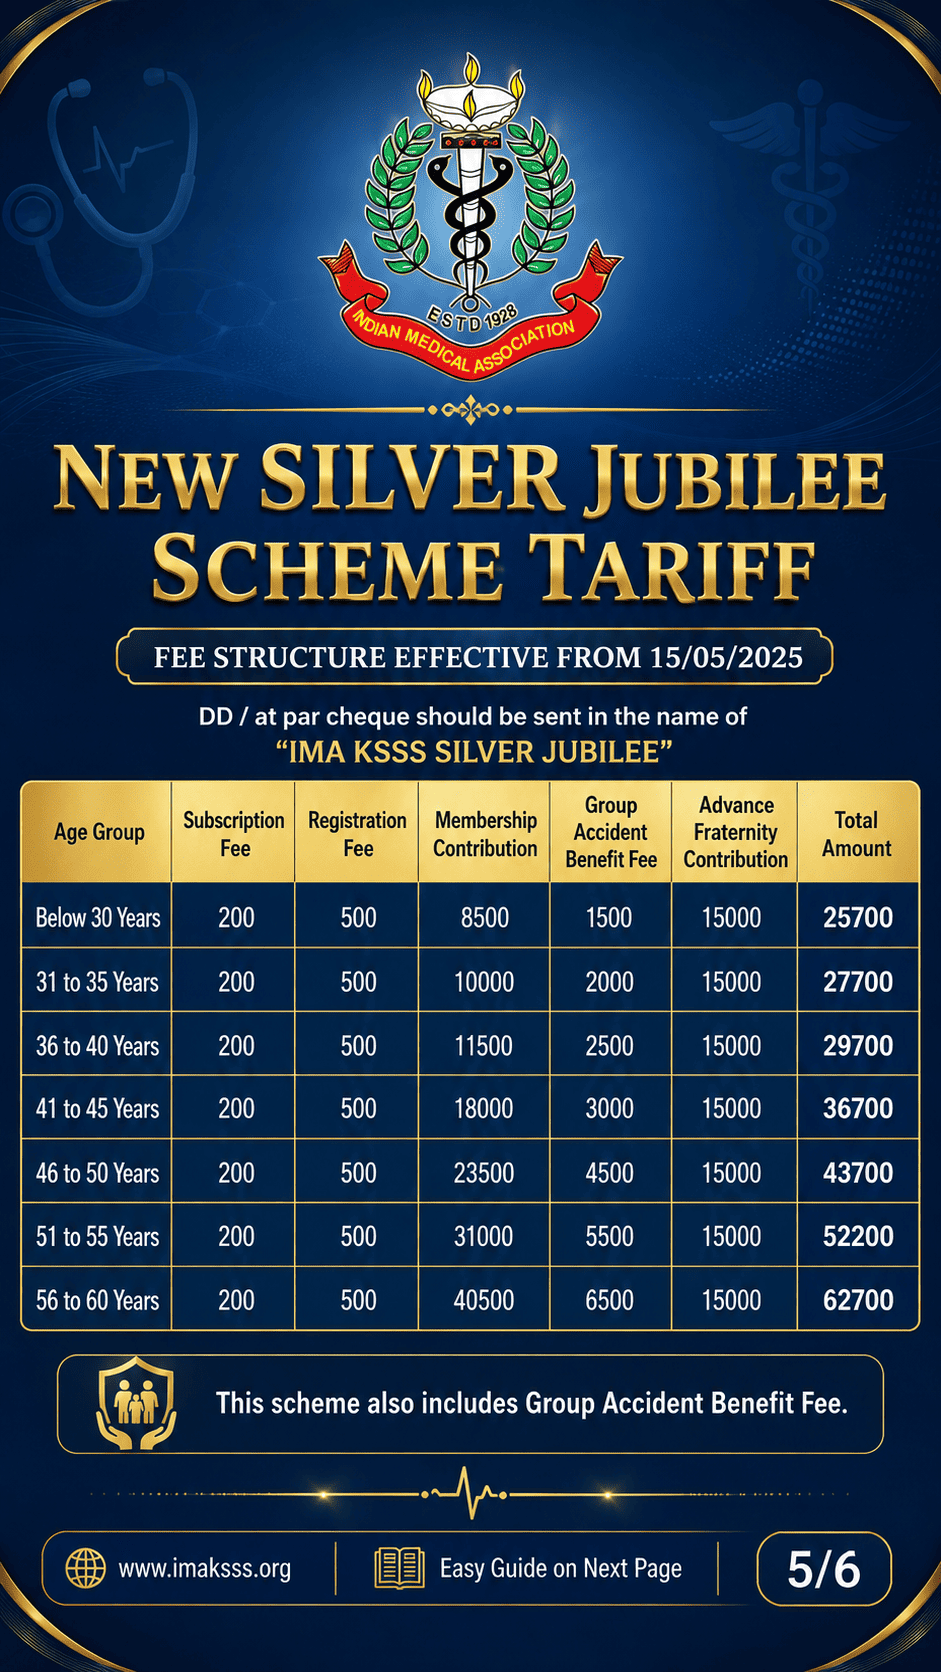
  • IMA Karnataka Social Security Scheme (KSSS)
    Admin IMA HubA Admin IMA Hub

    k0 (1) (1).png
    k1 (1).png
    k2 (1).png
    k3 (1).png
    k4 (1).png
    k5 (1).png
    k6 (1).png

    IMA KSSS — Is Your Family Protected?

    As doctors, we spend our lives protecting patients and their families. But one important question deserves our attention:

    If something happens to us, how financially secure is our own family?

    The IMA Karnataka Social Security Scheme (KSSS) has been built on the principle of mutuality — IMA members supporting the family of a fellow doctor during difficult times.

    The scheme currently offers two options:

    • Old Existing Scheme
    • Silver Jubilee Scheme

    The recently shared KSSS material highlights:

    • Enrollment available for eligible IMA members
    • Age-based admission contribution
    • Silver Jubilee Scheme tariff effective from 15 May 2025
    • Recent death benefit under Old Existing Scheme: ₹21.33 lakh
    • Recent death benefit under Silver Jubilee Scheme: ₹74.35 lakh
    • Continued fraternity contribution and active membership remain important for maintaining scheme benefits

    Each One Get One

    KSSS becomes stronger when more doctors participate.

    If you are already a member, consider speaking to one doctor colleague who has not yet joined. Explain the scheme, share the information, and help them understand how collective participation can strengthen financial security for doctors' families.

    Discussion for IMA Members

    Do you think every IMA member should consider joining a social security scheme such as KSSS?

    What prevents more doctors from enrolling?

    Is it:

    • Lack of awareness?
    • Difficulty understanding the contribution structure?
    • Delayed decision-making?
    • Need for better communication at branch level?

    Share your thoughts and experiences below. Your feedback can help us improve awareness and strengthen the scheme for the entire IMA fraternity.

    One Doctor. One Colleague. One Stronger IMA Family.

    IMA KSSS Contact: 9483991027
    Website: www.imakssshubli.org


  • If Every Doctor Stopped for Just One Day
    Admin IMA HubA Admin IMA Hub

    ima. (1).png
    Doctors are often discussed in terms of consultation fees, waiting time, outcomes, complaints and expectations.

    But rarely do we pause to consider a more fundamental question:

    What would happen if every doctor stopped working for just one day?

    No outpatient consultations.
    No elective or emergency surgeries.
    No critical-care decisions.
    No trauma response.
    No reassurance for anxious families.
    No one to take responsibility when a patient’s condition suddenly deteriorates.

    Within hours, emergency departments would become overwhelmed. Ambulances would have nowhere to transfer patients. People with heart attacks, strokes, injuries, infections, pregnancy-related complications and chronic illnesses could face serious consequences.

    This is not an argument that doctors should never be questioned. Accountability, ethics, communication and patient safety remain essential.

    But accountability must coexist with respect.

    Behind every consultation are years of education and training. Behind every prescription is professional responsibility. Behind every emergency decision is the possibility of legal scrutiny, public criticism and emotional burden.

    Doctors are expected to remain calm when patients are frightened, make decisions with incomplete information, work through nights and emergencies, and continue serving even when they are exhausted themselves.

    A question worth discussing

    Society expects doctors to be available whenever life is at risk.

    But are we creating a healthcare system that adequately respects, protects and supports those carrying that responsibility?

    The strength of healthcare does not depend only on buildings, equipment or technology.

    It also depends on whether healthcare professionals feel valued, safe and supported enough to continue serving.

    IMA HUB Discussion

    What needs to change to build a healthier relationship between doctors, patients, hospitals and society?

    When those who protect life are not adequately protected and respected, can the healthcare system remain strong?


  • Government Health Schemes Under Pressure: Can Private Hospitals Continue Without Financial Reform?
    Admin IMA HubA Admin IMA Hub

    ima (1).png
    Government health schemes were created to make quality treatment accessible to millions of beneficiaries.

    Private hospitals became essential partners in this mission by providing specialist consultations, surgeries, cancer care, emergency services and advanced treatment where public-sector capacity was limited.

    But an important question is now emerging:

    Can hospitals continue serving government-scheme patients when reimbursement rates do not reflect actual treatment costs and payments remain pending for long periods?

    Why this discussion matters

    A recent Economic Times report suggests that some leading private hospital groups are reassessing their participation in government health programmes because of low reimbursement rates, delayed payments, pricing restrictions and increasing pressure on working capital. While large hospital chains have not formally announced a complete withdrawal, some have reported financial impact, capped scheme volumes or changed their payer mix. (The Economic Times)

    According to the report, government schemes such as CGHS and ECHS may contribute around 25% of revenue for many leading private hospitals. Industry estimates suggest that this contribution could fall by approximately 3–5% by the first quarter of FY27 through selective de-empanelment or restricted bed allocation. (The Economic Times)

    What hospitals are facing

    The reported concerns are not limited to profitability alone.

    Hospitals participating in government schemes may have to manage:

    • Package rates that may not match current costs of medicines, implants, consumables, manpower and infrastructure.
    • Long settlement cycles and delayed reimbursement.
    • Deductions or claim rejections after treatment has already been provided.
    • Price caps on drugs and procedures.
    • Significant working-capital pressure.
    • Difficulty maintaining the same quality standards at unsustainable package rates.

    Max Healthcare reportedly estimated a substantial continuing revenue impact associated with CGHS arrangements, including discount requirements on chemotherapy medicines. Narayana Health has also reportedly controlled scheme volumes in some hospitals because of payment delays and reimbursement restrictions. (The Economic Times)

    The larger concern

    This should not become a debate between patient welfare and hospital sustainability.

    Both are interconnected.

    If reimbursement systems become financially unviable, hospitals may:

    • Limit the number of scheme beds.
    • Restrict certain high-cost procedures.
    • Delay expansion of services.
    • Prefer patients with faster payment cycles.
    • Voluntarily leave selected schemes.

    This could ultimately reduce treatment choices for government employees, pensioners, defence personnel and other beneficiaries who depend on empanelled hospitals.

    What requires urgent attention

    A sustainable government–private healthcare partnership requires:

    1. Scientific package-rate revision

    Rates must be periodically updated using actual treatment costs, inflation, staff expenses, medicine prices, implant costs and quality requirements.

    2. Time-bound claim settlement

    Hospitals should receive payment within a defined period, with transparent tracking and accountability for delays.

    3. Standardised deductions and rejection rules

    Claims should not be reduced using unclear or inconsistent interpretations after services have been delivered.

    4. Separate pricing for complex cases

    Cancer care, intensive care, trauma, implants and high-risk procedures may require flexible or severity-linked reimbursement.

    5. Digital transparency

    Hospitals should be able to track claim submission, queries, approval, deductions and payment status through a common digital system.

    6. Representation of treating hospitals

    Rate revisions and operational rules should involve clinicians, hospital administrators, professional bodies and smaller nursing homes—not only large chains.

    Important issue for smaller hospitals

    Large corporate hospitals may have stronger cash reserves and diversified revenue sources.

    Small and medium-sized hospitals, however, may face a greater risk. When payments remain pending for months, they must still pay salaries, vendors, pharmacies, laboratories, utilities and statutory expenses.

    For such hospitals, delayed reimbursement is not merely an accounting issue—it can directly affect continuity of services.

    Discussion

    Government schemes are essential for expanding healthcare access. Private hospitals are equally essential for delivering that care.

    The real solution is not withdrawal—it is the creation of a fair, transparent and financially sustainable partnership.

    Members are invited to share:

    • What percentage of your hospital’s patients come through government schemes?
    • What is the average payment delay in your institution?
    • Which schemes have the highest deductions or rejection rates?
    • Are current package rates sufficient for maintaining quality?
    • Should IMA develop a structured representation on reimbursement rates and delayed payments?

    Please share practical experiences without disclosing patient-identifiable or confidential claim information.

    Source: Economic Times report dated 7 May 2026. This forum post is intended for professional discussion and does not represent a conclusion that any hospital group has formally withdrawn from a government scheme. (The Economic Times)



  • Medicolegal Discussion: When Does POCSO Reporting Duty Begin?
    Admin IMA HubA Admin IMA Hub

    ml (1).png
    A 15-year-old girl comes for an ultrasound with abdominal pain and missed periods. The scan confirms pregnancy.

    For the radiologist, the examination may initially appear to be a routine diagnostic procedure. But when the patient is a minor, an important medicolegal question immediately arises:

    Does the discovery of pregnancy automatically mean that the doctor must report a POCSO offence?

    This question recently came before the Chhattisgarh High Court after a radiologist was prosecuted for allegedly failing to report the pregnancy of a minor under Sections 19 and 21 of the POCSO Act.

    What the Court clarified

    The High Court observed that the reporting obligation under Section 19 arises when a person has:

    Actual knowledge of a child sexual offence, or
    reasonable grounds to suspect that such an offence has occurred.

    The mere discovery of pregnancy during an ultrasound does not, by itself, prove that the doctor knew a sexual offence had been committed.

    Criminal prosecution cannot be based only on assumptions or presumptions.

    The Court therefore quashed the proceedings against the radiologist. However, the prosecution against the main accused continued independently.

    What doctors must understand

    This judgment should not be interpreted as permission to ignore pregnancy in a minor.

    Pregnancy below 18 years is a serious clinical and safeguarding concern. The doctor must carefully assess the history, surrounding circumstances, accompanying persons, disclosures made by the child and any signs suggesting coercion, exploitation or abuse.

    Where there is actual knowledge or reasonable suspicion of a POCSO offence, reporting to the local police or Special Juvenile Police Unit should not be delayed.

    Practical medicolegal safeguards

    1. Record the patient’s age and identity carefully.

    2. Document the history exactly as provided, without adding assumptions.

    3. Note who accompanied the child and who provided the history.

    4. Record any disclosure, inconsistency, coercion, fear or suspicious circumstance.

    5. Maintain confidentiality, but understand that mandatory reporting obligations may override routine confidentiality.

    6. Escalate doubtful cases through the hospital’s designated clinical, administrative or medicolegal pathway.

    7. When reasonable suspicion exists, report promptly and document when, how and to whom the report was made.

    The key takeaway

    Pregnancy alone may not automatically establish that a doctor had knowledge of a sexual offence. But pregnancy in a minor must never be treated as an ordinary finding without careful assessment, documentation and consideration of POCSO obligations.

    For doctors, the safest approach is not automatic prosecution or automatic silence. It is responsible clinical assessment, reasonable suspicion-based reporting and complete documentation.

    Discussion

    In your hospital, what protocol is followed when pregnancy is detected in a patient below 18 years?

    Does your institution have a written POCSO reporting pathway, designated nodal person and documentation checklist?

    Share your practical experience so that hospitals and doctors can learn from one another.

    For professional awareness and discussion only. Individual cases should be managed according to applicable law, institutional policy and appropriate legal guidance.


  • Why Every Practising Doctor in Karnataka Must Understand KPME, Package Rates and Costing — A Conversation with Dr. Pavan Patil
    Admin IMA HubA Admin IMA Hub

    pp (1).png

    Podcast | Policy, KPME & the Economics of Practice
    *A conversation with Dr. Pavan Patil -General Surgeon, Managing Director of Dr N B Patil Hospital (Gadag), and present member of the Karnataka Medical Council

    🎥 **Watch here:**https://youtu.be/nB4J5jZUx0Q?si=CHgEUch9j0RqnToA

    Most of us learn about a regulation only after it has already changed how we practise. This conversation is an attempt to reverse that order.

    1. The 2017 agitation — and what it actually was.
    KPME did not arrive in 2017; it has existed since 2007. What came in 2017 were amendments, drafted from a 2015 proposal and pushed towards the assembly without carrying the earlier committee recommendations forward. Dr. Pavan Patil takes us inside the discussions at the IMA State Conference, the days on the street, and the four-day fast in Belagavi — and, more usefully, what was won at the negotiating table afterwards, including the three expert committees written into the amended Act.

    2. Legal literacy is now part of clinical competence.
    His argument is blunt: we are not expected to master every law in this country, but we cannot afford to be ignorant of the ones that govern our own profession. If you cannot answer when questioned, you will be answered for.

    3. The costing problem.
    This is the heart of the episode. He describes a government meeting where an IVF package was fixed at ₹1.2 lakh with no stated costing basis — the answer to "on what basis?" being, in effect, that a few people had agreed to it. He points to the costing protocol already published under the central clinical establishment framework, the tables he worked through to build a defensible cost model, and the twenty-odd IVF practitioners he brought onto a call, because a package rate is nearly impossible to revise upward once notified. He contrasts scheme reimbursements — a caesarean in the ₹9,000–12,000 range, an inguinal hernia around ₹34,000 — with what the same procedure costs the state in a government hospital.

    4. Capping, and the case before the Supreme Court.
    A petition on private hospital charges is pending, with judgment possibly due in the coming months. His view: capping without understanding the cost structure of small and medium hospitals — and without fixing the absent referral system that sends patients straight to super-specialists — treats the symptom and worsens the disease.

    5. Medico-legal protection you should already know about.
    Following the Jacob Mathew guidelines, Karnataka has an SOP for police handling of complaints against doctors: a district-level complaint must be referred to the district medical board, which examines the case and gives its opinion, typically within 15–30 days. Also covered — unregistered practice and KPME's authority over it, the fire NOC rules issued in haste after a court order, and why the general practitioner deserves standing again within our own fraternity first.

    6. Why fragmentation costs us.
    In Australia, no health policy moves without consulting the medical association. Here, dozens of small associations mean the government can consult one, pass the policy, and call it consultation. His current mission is narrow and specific: get the three KPME expert committees actually activated, because most of these disputes ultimately land there.

    Approximate chapters
    📌 Episode Chapters:

    0:00 - Preview: Key Highlights
    1:54 - Introduction: Dr. Pavan Patil
    2:41 - The Fast Unto Death: What Triggered It
    3:05 - How Government Bypassed Judicial Committee Recommendations
    4:07 - The Belagavi Assembly Showdown
    6:40 - The Politician's Challenge & Dr. Patil's 4-Day Hunger Strike
    7:31 - Disputed KPME Provisions: What Doctors Were Fighting Against
    8:01 - Patients Could Complain for Long Waiting Times & Rude Tone
    8:31 - Government Price Caps on Private Practice
    10:51 - Resolution: 8 Out of 10 Demands Dropped
    13:27 - Why He Entered the Karnataka Medical Council (KMC)
    14:13 - Winning the KMC Elections in 2020
    14:47 - What Medical Councils Actually Do
    15:19 - Ethics, Misconduct & Quasi-Judicial Powers of KMC
    17:09 - What Happens When Police Receive a Complaint Against a Doctor
    17:29 - Jacob Mathew Judgment: No FIR Without Medical Board Opinion
    20:21 - How KMC Cleared Its Case Backlog
    21:09 - Three Specialized Hearing Halls: How It Works
    23:11 - India Has No Referral System — The Real Problem
    26:05 - Why Patients Skip Primary Care & Go Straight to Super-Specialists
    28:00 - Reviving General Practice in India
    29:00 - University-Recognized Fellowships in Family Medicine
    31:06 - Tackling Quackery: Surprise Inspections & FIRs
    37:40 - How Healthcare Costs Are Actually Calculated
    38:14 - Why Small Nursing Homes Are Undercharging
    41:25 - How AI Was Used to Calculate Real IVF Package Costs
    42:15 - Realistic IVF Cost: ₹3.5 Lakh Explained
    43:13 - Government Spends ₹1.5 Lakh on a C-Section — Pays Private Only ₹9,000
    47:36 - Scheme Rates Based on 1981 Tender Figures
    49:05 - Hernia Pays More Than Splenectomy: The Absurd Rate Card
    51:19 - Why Government Hospitals Should Issue Itemized Bills
    52:48 - Educating Patients on True Healthcare Costs
    1:06:10 - Fire NOC: How Small Clinics Were Being Strangled by Compliance
    1:08:31 - How This Rule Was Fixed Across Government Departments
    1:16:13 - Final Message to Young Doctors
    1:16:26 - Why Every Doctor Should Spend Time in IMA or KMC

    Final inputs for the doctors

    1. Read your own Act. One evening with the KPME Act and its amendments will serve you better than a decade of forwarded interpretations. Add the Clinical Establishments rules and your registration conditions.

    2. Know your costs before someone else fixes them. Work out what a caesarean, a hernia repair, a dialysis cycle actually cost you — manpower, consumables, overheads, depreciation. When package rates are negotiated, the fraternity that arrives with a costing sheet is the one that gets heard. Opinions lose to spreadsheets.

    3. Keep the medico-legal SOP where your staff can find it. Every complaint of alleged negligence must go through the district medical board. Your front desk and duty medical officer should know this before the day it is needed, not after.

    4. Stop negotiating alone. If a rule or an inspection is causing you difficulty, it is almost certainly causing forty other members the same difficulty. Bring it to the branch. Individual representation gets an individual exception; collective representation changes the rule.

    5. Young doctors — give the profession two hours a month. The first years go into building your practice, and that is right. But the terms on which you will practise for the next thirty years are being written now, in committee rooms, by whoever chose to show up. Show up.


    If you have faced a KPME inspection issue, a scheme package that does not cover cost, or a police complaint routed incorrectly, post it below. Patterns are what make a case.

    Note: Figures and interpretations in this episode are as stated by the speaker. Please verify current provisions against the Act, rules and official circulars before relying on them in practice. Keep all case references de-identified.


  • CCI Closes Decade-Long Case Against 12 Delhi-NCR Hospitals — No Abuse of Dominance Found
    Admin IMA HubA Admin IMA Hub

    cci closed long decade case.png

    In a landmark ruling dated May 21, 2025, the Competition Commission of India (CCI) has officially closed abuse of dominance proceedings against 12 major super-speciality hospitals in the Delhi-NCR region, bringing an end to a nearly 10-year investigation.

    The hospitals include Max Super Specialty Hospital (Patparganj, Saket, Shalimar Bagh), BLK Max Super Specialty Hospital, Fortis Flt. Lt. Rajan Dhall Hospital, Fortis Escorts Institute and Research Centre, Sir Ganga Ram Hospital, Indraprastha Apollo Hospital, St. Stephen's Hospital, and Batra Hospital & Medical Research Centre, among others. Devdiscourse

    📋 Background
    The case originated from a complaint filed in 2014–15 alleging that these hospitals were exploiting their dominant positions by forcing patients to purchase medicines, consumables, and medical devices from in-house pharmacies at prices several times higher than open-market rates. PNI
    The CCI initially ordered an investigation. The Director General (DG) examined all 12 hospitals and concluded they were dominant — but the Commission ultimately disagreed with those findings. Bar and Bench

    ⚖️ What the CCI Decided
    The CCI defined the relevant market as the provision of in-patient healthcare services by super-speciality hospitals across the Delhi-NCR region — not each individual hospital as a separate market. India Legal
    The Commission also observed that medicines, consumables, and medical devices form part of bundled hospital treatment and are not purchased by patients as standalone products. India Legal
    On pricing, the CCI applied the two-stage "United Brands" test — requiring proof that prices were both excessive and unfair — and found that the DG had incorrectly treated excessive pricing as automatically unfair, which is an insufficient legal standard. Devdiscourse
    The CCI also rejected comparisons between hospital rooms and hotel rooms, noting that hospital rooms are integral to clinical infrastructure supported by medical staff, emergency systems, and continuous patient monitoring. India Legal

    💬 Why This Is Controversial
    Not everyone agrees with the outcome. Critics argue the ruling raises a fundamental question: once a patient is admitted, do they remain a patient — or become a captive customer? Before admission, a patient may theoretically be in a competitive market, but after admission, the hospital controls their care environment entirely. Telangana Today
    The CCI appears to have accepted that admitted patients rely on internal hospital ecosystems, yet concluded this does not constitute actionable abuse under competition law. Telangana Today

    🔍 Key Takeaways for Discussion

    Should "captive consumer" dynamics post-admission be treated differently under competition law?
    Is the two-stage excessive + unfair pricing test adequate to protect patients?
    Does defining the market broadly (all Delhi-NCR super-speciality hospitals) undermine patient protection in practice?
    What regulatory mechanisms beyond competition law can address hospital pricing transparency?

    📌 Source: ETHealthworld / Economic Times | Bar & Bench | India Legal Live
    Drop your thoughts below — is this a win for the healthcare sector, or a gap in patient protection law?


  • India Takes a Major Step Forward — Childhood Cancer Registry in the Works | 75,000 Kids Diagnosed Every Year
    Admin IMA HubA Admin IMA Hub

    CANCER RX.png

    The Big News
    India's Union Ministry of Health and Family Welfare, in collaboration with the Indian Council of Medical Research (ICMR), is working to establish a dedicated nationwide Childhood Cancer Registry. The goal is to ensure no child battling cancer goes untracked, undiagnosed, or untreated.
    As stated by Leimapokpam Swasticharan, Deputy Director General of the Directorate General of Health Services (DGHS): "One of the key priorities in childhood cancer care is early detection. Setting up a registry for childhood cancer and declaring it a notifiable disease is an issue. We are still working with ICMR on this. The aim is not to miss any patient." Thehonanews

    The Scale of the Problem
    This initiative comes against a deeply worrying backdrop. India currently records around 75,000 new childhood cancer cases every year — a number that underscores a serious public health challenge that has long been under the radar.
    The most common cancers affecting children in India include:

    Leukaemia (blood cancer)
    Brain tumours
    Lymphomas

    A major problem is that most children are diagnosed only at advanced stages, which drastically reduces treatment effectiveness and survival chances.

    Why a Registry Matters
    Right now, India lacks comprehensive, reliable data on paediatric cancer cases at a national level. Without this data:

    Healthcare policy cannot be effectively designed
    Resources cannot be directed where they are most needed
    Trends cannot be identified or acted upon

    The initiative aims to improve early detection, ensure comprehensive reporting, and potentially make childhood cancer a notifiable disease — addressing significant gaps in diagnosis across the country. PNI
    Making it a notifiable disease would legally require doctors and hospitals to report every case to the government, plugging a major data gap that currently allows thousands of cases to slip through the cracks.

    The Early Detection Push
    One of the most critical goals of this initiative is improving early diagnosis. Childhood cancer symptoms — fatigue, unexplained weight loss, persistent fever, unusual lumps — are often mistaken for common illnesses, leading to dangerous delays.
    The registry is expected to support:

    Awareness campaigns for parents and communities on warning signs
    Training upgrades for healthcare workers on identifying and referring paediatric cancer cases
    Community outreach programs to reduce stigma and encourage families to seek timely care

    Challenges Ahead
    This is not going to be easy. Key hurdles include:

    Geographic diversity — Tracking cases consistently across India's vast and varied healthcare infrastructure is a massive logistical challenge
    Social stigma — In many communities, a cancer diagnosis still carries shame, discouraging families from reporting or seeking care
    Infrastructure gaps — Smaller towns and rural areas often lack the specialists needed to even identify paediatric cancers

    The government's plan includes partnering with NGOs and community leaders to bridge these gaps and build local trust.

    A Global Context
    Internationally, childhood cancer survival rates in high-income countries exceed 80%, largely due to strong cancer registries, early detection systems, and targeted treatment protocols. India's survival rates remain significantly lower — not because treatment is impossible, but because cases are caught too late and data to guide policy is missing.
    A first step was already taken earlier this year when the Cancer Institute (WIA) in Chennai launched India's first dedicated population-based childhood cancer registry, recording an incidence rate of 136 per million children in the Greater Chennai zone, with a 2-year survival rate of 60% for all registered patients. The proposed national registry would scale this model across the entire country. who

    What This Means Going Forward
    If implemented effectively, the Childhood Cancer Registry could:

    Enable data-driven policy for paediatric oncology
    Improve survival rates through earlier detection and standardised treatment
    Help identify which regions and demographics are most at risk
    Strengthen collaboration between hospitals, research institutions, and government bodies

    Your Thoughts?
    This is a policy that could genuinely save tens of thousands of young lives. But the success will depend entirely on execution — adequate funding, inter-state coordination, and community trust.
    Do you think making childhood cancer a notifiable disease is the right approach? Should India look at existing international models like those in the UK or USA? Share your thoughts below.

    Sources: Ministry of Health & Family Welfare (India), ICMR, DGHS, IARC


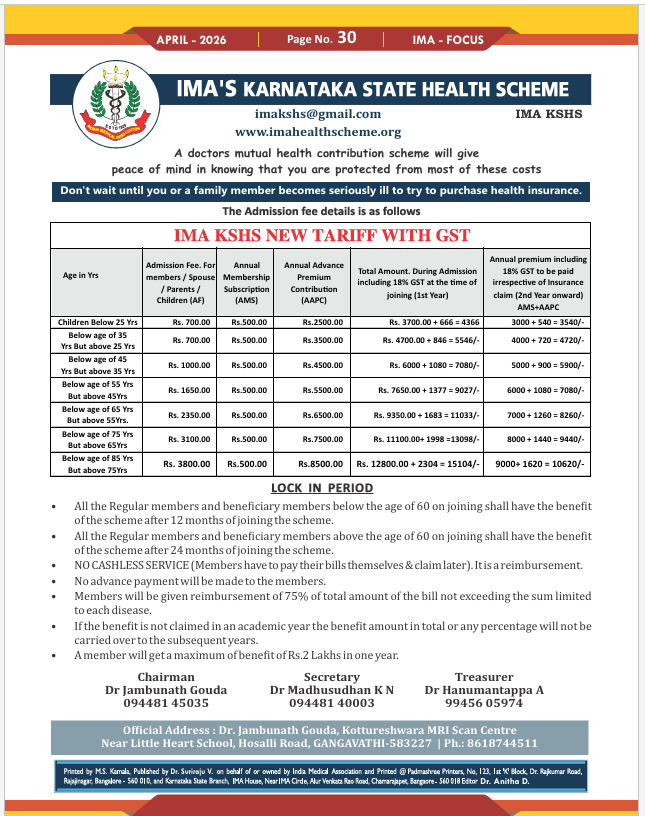
  • Three IMA Schemes Every Karnataka Doctor Should Know — Legal Cover, State Health, and National Health
    Admin IMA HubA Admin IMA Hub

    ksps shceme_15.07.26_REC.png kshs scheme_15.06.49_REC.png

    Practicing medicine in India today means accepting two uncomfortable realities: a single legal notice can wipe out years of savings, and a sudden hospitalization can drain family finances even faster.

    The IMA runs three schemes that address both — one for legal defense, and two health schemes (state and national) that most members don't realize can be enrolled in simultaneously for higher combined coverage.

    1. IMA-KPPS — Karnataka Professional Protection Scheme

    A mutual legal-defense fund for medical practitioners facing consumer complaints, professional negligence claims, and compensation demands.

    What it does

    • Provides protection up to ₹1 Crore per member
    • Fights cases at District, State, and National Consumer Commission levels
    • Covers professional negligence and CPA (Consumer Protection Act) awards

    Who is covered

    • Individual doctors only — not the hospitals where they practice
    • Pathologists and Microbiologists are eligible — but their labs are not

    Important caveats

    • Membership is not automatic; it requires Managing Committee approval
    • The cause of action must fall within an active membership period
    • Continuous membership is mandatory to claim scheme benefits
    • Members must stay in constant contact with the appointed advocate and submit case papers, investigation reports, and treatment records along with the legal notice

    Cost

    • One-time admission: ₹3,700
    • Annual premium notice dispatched on or before April 1st each year

    Contact

    • 📞 9141546924 / 080-26705447
    • ✉️ imakpps@gmail.com
    • 🌐 www.imakppsbengaluru.org

    A national counterpart — IMA NPPS (National Professional Protection Scheme) — is also available at nimapps.com for doctors who prefer national-level coverage.


    2. IMA-KSHS — Karnataka State Health Scheme

    A mutual health-contribution scheme covering the member and immediate family on a reimbursement basis.

    Coverage

    • Member, spouse, parents, and children
    • 75% reimbursement of medical bills (with per-disease caps)
    • Maximum annual benefit: ₹2 Lakhs
    • Reimbursement only — no cashless facility, no advance payments. Members pay first and claim later.
    • Unused benefit does not carry forward to the next year

    Lock-in period before claims

    • Joining below age 60: 12 months
    • Joining above age 60: 24 months

    Premium structure (admission year + 2nd year onwards, inclusive of 18% GST)

    Age band Total at admission 2nd year onwards
    Below 25 yrs ₹4,366 ₹3,540
    25 – 35 yrs ₹5,546 ₹4,720
    35 – 45 yrs ₹7,080 ₹5,900
    45 – 55 yrs ₹9,027 ₹7,080
    55 – 65 yrs ₹11,033 ₹8,260
    65 – 75 yrs ₹13,098 ₹9,440
    75 – 85 yrs ₹15,104 ₹10,620

    Important: KSHS premiums escalate steeply with every age band — joining late costs significantly more over the long run.

    Contact

    • 📞 8618744511 / 094481 45035
    • ✉️ imakshs@gmail.com
    • 🌐 www.imahealthscheme.org

    3. IMA-NHS — National Health Scheme

    The IMA's pan-India mutual health scheme, approved by the Central Council in 2014 and operational since 2015, covering members along with their spouse, children, and parents during hospitalization.

    Three things that make NHS genuinely distinctive

    1. Pre-existing diseases are covered from day one — including Cancer, cardiac conditions, lifestyle diseases, and Organ Transplant. Most private insurers either exclude these or impose multi-year waiting periods.
    2. No medical examination required to join — regardless of age or existing conditions.
    3. Premium does not escalate as you age within a slab. A doctor joining at 25 keeps paying the same ₹3,500 renewal until age 55. Compare this to KSHS, where every band brings a hike.

    Eligibility & flexibility

    • Joining age extends up to 80 years — far beyond the typical 65-year cap on other schemes
    • Immediate relatives of IMA life members are also eligible
    • Original bills are returned on request with a self-addressed stamped cover, so a single hospitalization can be submitted to multiple schemes

    Coverage & reimbursement

    • 75% of total bill reimbursed, capped at ₹2 Lakhs per year (with plans to scale up to ₹2.5–3 lakhs as membership grows)
    • Treatment cost must exceed ₹5,000 to trigger a claim
    • Reimbursement-only; no cashless

    Premium structure

    At joining (1st year, with one-time admission fee)

    Age Admission AMS AFAC Total
    Below 25 ₹1,000 ₹500 ₹2,500 ₹4,000
    25 – 35 ₹1,000 ₹500 ₹3,000 ₹4,500
    35 – 45 ₹1,250 ₹500 ₹3,000 ₹4,750
    45 – 55 ₹1,750 ₹500 ₹3,000 ₹5,250
    55 – 60 ₹5,000 ₹500 ₹5,000 ₹10,500
    60 – 65 ₹7,000 ₹500 ₹7,000 ₹14,500
    65 – 70 ₹8,000 ₹500 ₹8,000 ₹16,500
    70 – 80 ₹10,000 ₹500 ₹10,000 ₹20,500

    Renewal (2nd year onwards — admission fee is one-time only)

    Age slab AMS AFAC Total
    Below 25 ₹500 ₹2,500 ₹3,000
    25 – 55 ₹500 ₹3,000 ₹3,500
    55 – 60 ₹500 ₹5,000 ₹5,500
    60 – 65 ₹500 ₹7,000 ₹7,500
    65 – 70 ₹500 ₹8,000 ₹8,500
    70 – 80 ₹500 ₹10,000 ₹10,500

    Contact

    • 🌐 www.imanhs.com

    ⭐ The Most Overlooked Strategy — Stack NHS + KSHS

    This is the single most underused fact among Karnataka IMA members:

    NHS explicitly permits members to also enrol in other insurance schemes and State Health Schemes — and notes that combining State HS (₹3L) with National HS (₹2L) gives up to ₹5 Lakhs of total annual benefit.

    For Karnataka doctors, this translates to:

    • Enrol in KSHS (state) → ₹2 Lakhs coverage
    • Enrol in NHS (national) → ₹2 Lakhs coverage
    • File the same hospital bills under both (NHS returns originals so you can claim elsewhere)
    • Effective combined cover: up to ~₹4–5 Lakhs/year

    Add a separate private mediclaim policy on top of this for catastrophic-tier coverage (₹10L+), and a doctor's family is reasonably well-protected without paying enterprise insurance premiums.


    Quick Comparison

    IMA-KPPS IMA-KSHS IMA-NHS
    Type Legal protection State health National health
    Max benefit ₹1 Crore ₹2 Lakhs/year ₹2 Lakhs/year (₹3L target)
    Family covered? No Yes Yes
    Pre-existing diseases N/A Not explicit Covered (incl. Cancer, Cardiac, Transplant)
    Medical test to join N/A Not required Not required
    Max joining age N/A 85 80
    Reimbursement rate N/A 75% 75%
    Cashless? N/A No No
    Premium escalates with age? N/A Yes (steeply) No (flat within slab)
    Stackable with others? N/A Yes Yes — explicitly
    Admission fee ₹3,700 flat ₹700 – ₹3,800 ₹1,000 – ₹10,000

    Worth Discussing

    A few questions for the community:

    • For those enrolled in KPPS — has the legal support been responsive when you actually needed it?
    • Has anyone successfully stacked NHS + KSHS on the same hospitalization? How did the dual-claim process actually work?
    • KSHS vs NHS reimbursement turnaround — which is faster in practice?
    • For younger doctors: enrol early in IMA schemes, or just buy comprehensive private mediclaim and skip these?
    • Anyone with experience of a catastrophic claim (say >₹5L) — how did the stacking actually pay out?

    If you're a Karnataka-based IMA member, all three schemes are worth a closer look — before you need them, not after.


    Sources: IMA Focus bulletin, April 2026 (KPPS & KSHS details); IMA India official website — ima-india.org/ima/left-side-bar.php?pid=703 (NHS details). Please verify current figures and eligibility directly with the respective scheme offices before enrolling.


  • Medico-Legal Cases, Medical Negligence, and the 2026 Supreme Court Ruling on Posthumous Liability — A Working Note for Practising Doctors
    Admin IMA HubA Admin IMA Hub

    medicolegal.png

    A primer on what a Medico-Legal Case actually is, how to handle one without exposing yourself, the statutory architecture that governs negligence in India, and what the Supreme Court's recent judgment in Kumud Lall changes for every clinician — and their family.

    1. The 2026 Ruling, Explained Properly
    On 4 May 2026, a Bench of Justices J.K. Maheshwari and Atul S. Chandurkar delivered judgment in Kumud Lall v. Suresh Chandra Roy (Dead) Through LRs, 2026 INSC 443. Most of the social-media coverage has reduced this to a single line — "your family will pay your negligence bills." That framing is incomplete and, in places, wrong. The ruling is more nuanced, and the nuance is what matters for clinical practice and personal financial planning.

    The factual matrix
    A complaint was lodged in 1997 alleging that surgery performed in 1990 by Dr. P.B. Lall had cost the patient vision in one eye. The District Forum awarded ₹2.6 lakh; the State Commission reversed, citing absence of expert evidence and the alternative diagnosis of glaucoma. While the matter was pending in revision before the NCDRC, Dr. Lall died in 2009. The complainant moved to substitute the doctor's wife and son as legal heirs. The NCDRC permitted substitution. The heirs appealed.

    The legal question
    Two doctrines were in collision. The common-law maxim actio personalis moritur cum persona — a personal cause of action dies with the person — would have ended the case. Against it stood Section 306 of the Indian Succession Act, 1925, which preserves causes of action that survive to and against the estate, and Order XXII Rule 4 of the CPC, which prescribes substitution of legal representatives.

    What the Court actually held
    The Supreme Court drew a careful distinction that doctors should understand precisely:
    Personal claims abate on death. Claims tied to the deceased's person — pain, mental suffering, reputational injury — die with the doctor. They cannot be pursued against the heirs.
    Pecuniary "loss to estate" claims survive. Where the alleged negligence has produced a financial loss that can be measured against the deceased's estate, the proceedings continue against the legal representatives.
    Heirs are not personally liable. They step into the shoes of the deceased only as representatives of the estate. Personal assets that did not come to them through inheritance from the doctor are out of bounds. Liability is capped at the value of the inherited estate.
    The earlier NCDRC view in Balbir Singh Makol v. Sir Ganga Ram Hospital (2001) was overruled to the extent it had treated all such claims as abating on death.

    In other words: the case does not "automatically end" when the doctor dies, but it does not "automatically continue against the family" either. The forum must first decide whether negligence occurred, then sort which heads of claim are personal (gone) and which are estate-based (recoverable, up to the inherited share).

    What this changes for you in practice

    • The window of legal exposure now extends past your lifetime. A complaint filed in your sixties can still be alive thirty years later, and your spouse and children can be brought on record.
    • Professional indemnity insurance suddenly carries a planning dimension — does your policy continue to respond once you are deceased and proceedings continue against the estate? Most older policies are silent on this. Speak to your insurer.
    • Estate planning is no longer a peripheral concern. The structure of your assets — what is jointly held, what is in a trust, what passes outside the estate — affects how much of an inheritance is exposed to a future negligence finding. This is a conversation with a lawyer, not with a forum.
    • Documentation done today protects your heirs tomorrow. The defensive value of a properly maintained file does not expire when you do.

    Judgments worth knowing in working detail
    Parmanand Katara v. Union of India (1989). Establishes the absolute primacy of life-saving over procedural compliance. An MLC label is not a brake on treatment.

    Jacob Mathew v. State of Punjab (2005). The cornerstone of criminal-negligence jurisprudence for doctors. Before a private criminal complaint against a doctor is entertained, the complainant must produce a credible opinion from another competent doctor in the same field. Routine arrest is impermissible. The standard of negligence under Section 304A is gross — mere error of judgment or a deviation that another competent professional might also have made does not cross the threshold.

    Martin F. D'Souza v. Mohd. Ishfaq (2009). Held that an unfavourable outcome — a failed surgery, an unexpected complication — does not, by itself, establish negligence. The doctrine of res ipsa loquitur is not to be applied mechanically against doctors. (Subsequently nuanced in V. Kishan Rao, but the central caution survives.)

    V. Kishan Rao v. Nikhil Super Speciality Hospital (2010). Clarified that expert evidence is not invariably required in every consumer-forum negligence case. In straightforward fact patterns — failure to diagnose an obvious condition, complete absence of basic care — the forum can decide without an expert. Expert opinion is necessary in genuinely technical disputes.

    Bolam v. Friern Hospital Management Committee (1957) and its Indian reception. A doctor is not negligent if she has acted in accordance with a practice accepted as proper by a responsible body of medical opinion in the relevant specialty. The Indian courts have adopted Bolam with the Bolitho (1997) caveat — the body of opinion must itself withstand logical analysis.

    Kumud Lall v. Suresh Chandra Roy (2026). Discussed in Section 1 above. The first authoritative ruling clarifying the survivability of consumer-forum medical-negligence claims against the estate of a deceased doctor.

    3. Practical Risk Management for Clinicians
    Defensive medicine — ordering investigations one does not believe are necessary, refusing to undertake legitimate procedures because of perceived medico-legal risk — is itself a form of harm. The goal is not to practise scared. It is to practise correctly and prove it.

    The shortlist that meaningfully reduces exposure:

    • Documentation discipline. Notes are made contemporaneously, not reconstructed. Consent is in writing and specific to the procedure, not a generic admission form. Investigations and their results are filed and dated. Telephonic instructions to nursing staff are read back, recorded, and countersigned at the next visit.
    • Standard of care. Where a treatment guideline exists (NMC, professional society, ICMR, WHO), follow it or document the clinical reason for departure. An undocumented departure is the most defensible-looking case turned indefensible at trial.
    • Communication. A large proportion of negligence complaints originate not in the clinical error itself but in the communication failure that followed. The patient who feels heard and informed sues less often than the patient who feels dismissed.
    • Consent that is genuinely informed. Material risks — the ones a reasonable patient in this position would want to know — must be discussed. A signed consent form does not establish informed consent if the conversation behind it never happened.
    • Indemnity cover. Re-examine your policy in light of the 2026 ruling. Confirm in writing with your insurer that the cover responds to claims pursued against your estate after death and that the sum insured is realistic for the procedures you actually perform.
    • Estate structuring. Discuss with a lawyer how your estate is held and how it would devolve. The point is not to defeat legitimate claims; it is to ensure that your family is not blindsided by a 2002-vintage complaint surfacing in 2032.
    • Appearance in proceedings. When summoned, attend. Absentee defence is the worst defence.

    The Kumud Lall judgment is being read in some quarters as a hostile development for the medical profession. It is more accurately read as the closing of a doctrinal anomaly — one in which a patient with a meritorious claim could find themselves remediless through the accident of the defendant's death, while another patient with an identical claim received compensation because the defendant happened to live longer. The Court has restored symmetry, while expressly protecting the heirs from any liability beyond what they have inherited.

    The clinical takeaway is the same as it has always been.
    Practise to the standard. Document as if it will be read back to you under cross-examination. Communicate with patients as people, not as future plaintiffs. And bring the ordinary disciplines of estate planning and indemnity into the same orbit of professional housekeeping that already includes registration, CME, and licence renewal.

Member List

Admin IMA HubA Admin IMA Hub
  • Login

  • Don't have an account? Register

  • First post
    Last post
0
  • Categories
  • Recent
  • Tags
  • Popular
  • Users
  • Groups